CJC-1295’s side effects are poorly measured. Its only controlled human trials found no serious reactions, but the FDA lists serious adverse events reported with it, including a raised heart rate and a systemic vasodilatory (flushing, blood-pressure) reaction. Fluid retention, wrist tingling and higher blood sugar are expected from raised growth hormone. It is not FDA-approved.
CJC-1295 is a synthetic, long-acting analog of growth-hormone-releasing hormone (GHRH), usually sold in the “DAC” form that binds albumin and stretches its half-life to days. It is not an FDA-approved drug, and the honest problem with cataloguing its side effects is that almost nobody has studied them properly. The ipamorelin & CJC-1295 evidence review covers what researchers have measured for efficacy. This page separates the limited human safety findings from effects inferred from the biology of a raised GH/IGF-1 axis.
What human data actually exist
The controlled human record is essentially one small study. Teichman and colleagues gave CJC-1295 to healthy adults in ascending-dose, placebo-controlled trials of 28 and 49 days and reported that a single injection raised mean plasma GH two- to tenfold for six days or more and IGF-1 1.5- to threefold for nine to eleven days, on an estimated half-life of 5.8 to 8.1 days — with no serious adverse reactions and a drug that was “relatively well tolerated.”[1] That is reassuring as far as it goes — but it was a pharmacokinetic and pharmacodynamic study in a few dozen people, not a trial powered or designed to detect harm, and it says nothing about months or years of use. So the correct starting posture is not “it looks safe” but “it has barely been studied.”
The FDA’s own compounding safety list adds a harder note. It says compounded CJC-1295 may pose a risk of immune reactions and impurity problems, and that the agency “has identified serious adverse events associated with CJC-1295 including increased heart rate and systemic vasodilatory reaction,” with “available clinical data” described as limited. CJC-1295 sits on the FDA’s “nominated but withdrawn” list, so as of October 2026 it is not cleared for pharmacy compounding.[5]
The commonly reported, milder effects
The effects most often described with GHRH-class peptides are local and vascular: injection-site reactions (redness, itching, a small welt), transient flushing, and headache. These are consistent with the pharmacology of a subcutaneously injected vasoactive peptide, and they map onto what is documented for approved GHRH analogs. Because CJC-1295 itself has not been characterized for these specifically beyond the “well tolerated” summary above, the better-described sibling profile lives on the sermorelin side-effects page — sermorelin being an approved, shorter-acting GHRH analog whose adverse-event profile is far better documented.
Water retention, tingling, and glucose: the GH-excess signature
The effects people worry about most are not unique to CJC-1295 — they are the classic consequences of pushing the GH/IGF-1 axis, and they are best characterized in states of chronic GH excess. Sustained GH promotes sodium and fluid retention, producing soft-tissue swelling and edema; the same soft-tissue expansion around the wrist is a recognized cause of carpal tunnel syndrome, which is the mechanism behind the tingling and numbness research users describe.[4] And GH is a counter-regulatory hormone: sustained elevation antagonizes insulin, raising the risk of insulin resistance and impaired glucose tolerance.[3] None of these has been measured in CJC-1295 users specifically — the point is that the drug’s entire mechanism is to raise the exact hormones that, in excess, drive these effects.
The DAC-specific concern: a raised trough, not a pulse
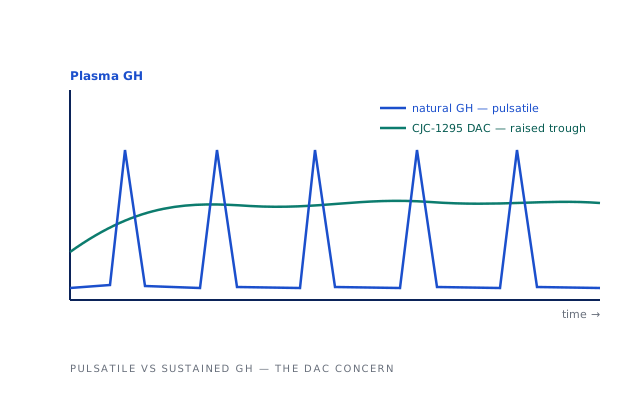
Here is the concern that is genuinely specific to the long-acting DAC form. Natural GH is secreted in sharp pulses that fall back to a near-zero baseline between peaks, and that pulsatile pattern is thought to matter for the hormone’s normal physiology. When Ionescu and Frohman gave a single CJC-1295 injection (60 or 90 micrograms per kilogram) to healthy men aged 20 to 40 and sampled GH overnight a week later, the pulses were preserved — their frequency and magnitude were unchanged — but basal (trough) GH rose roughly 7.5-fold (P < 0.0001). That raised interpulse floor contributed to a 46% rise in mean GH, and IGF-1 rose 45%.[2] In other words, the DAC version does not so much amplify the peaks as lift the valleys, shifting a naturally pulsatile signal toward a more continuous elevation.[1] Whether that chronically raised baseline carries the same long-term risk as GH excess is exactly the question no study of this peptide has answered.
Swipe to see all columns
| Reported effect | Evidence status for CJC-1295 | Basis |
|---|---|---|
| Injection-site reactions, flushing, headache | Not specifically characterized; overall 'well tolerated' in one small study | GHRH-class pharmacology; Teichman |
| Increased heart rate, systemic vasodilatory reaction | Serious adverse events the FDA says it has identified | FDA compounding safety list |
| Fluid retention / edema | Not measured in users; mechanistically expected | GH-excess physiology (Melmed) |
| Tingling / numbness (carpal-tunnel-like) | Not measured in users; mechanistically expected | Soft-tissue swelling in GH excess (Melmed) |
| Impaired glucose tolerance / insulin resistance | Not measured in users; mechanistically expected | GH antagonizes insulin (Melmed) |
| Raised trough (non-pulsatile) GH from the DAC | Demonstrated in humans | Ionescu & Frohman; Teichman |
The supply problem sits on top of all of this
Everything above assumes the vial contains pure CJC-1295 at the stated amount. It usually cannot be assumed. These peptides are sold almost entirely as “research-use-only”products made outside pharmaceutical manufacturing standards, which means the purity, sterility, actual dose, and even the identity of the contents are unverified. Contaminants, endotoxin, incorrect peptides, and inconsistent concentration are all realistic — and those risks are entirely separate from, and additional to, the peptide’s own pharmacology. A clean safety story about the molecule would not rescue a contaminated vial. This is why no discussion of dose belongs here; if you want to see how that same caution frames the numbers, the CJC-1295 & ipamorelin dosage page treats it the same way.
How this differs from ipamorelin
CJC-1295 and ipamorelin are frequently stacked but act at different points. Ipamorelin is a selective ghrelin-mimetic secretagogue that triggers a short GH pulse; CJC-1295 is the GHRH analog whose DAC form gives the sustained, trough-raising exposure described above. That difference matters for side effects: the DAC’s prolonged, non-pulsatile elevation is the concern unique to CJC-1295, whereas ipamorelin’s effects have their own profile — covered on the ipamorelin side-effects page.
The honest bottom line
CJC-1295’s side-effect profile is mostly a set of well-founded predictions, not a measured record. One small human study found it relatively well tolerated with no serious reactions,[1] though the FDA notes serious adverse events reported with it, including increased heart rate;[5] the fluid retention, carpal-tunnel-like tingling, and glucose effects are inferred from what sustained GH/IGF-1 excess reliably does;[3][4] and the DAC form’s signature move is to raise the between-pulse GH floor rather than preserve the natural low trough.[2] Layer on an unregulated supply chain of unknown purity, and the appropriate stance is caution and a clinician — not a stack assembled from a forum. Sermorelin, a GHRH analog that pharmacies can still compound, is the prescription route most telehealth services offer; the PlexusDx review shows it at $179 a month, or $129 on a six-month plan.