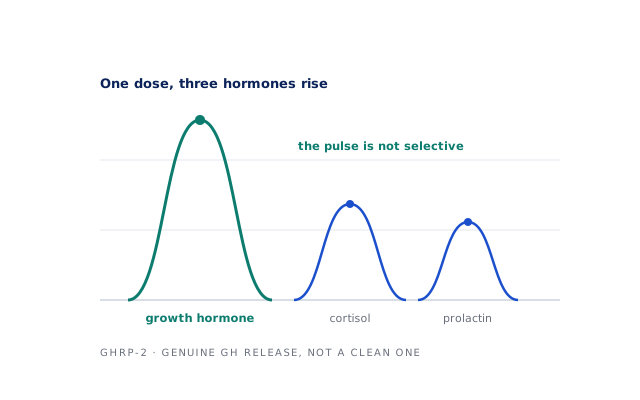
GHRP-2 (pralmorelin) is a synthetic ghrelin-receptor agonist that stimulates growth hormone. Human studies establish short-term hormone release and increased appetite; they do not establish lasting muscle gain, fat loss or anti-aging benefits. A diagnostic GH response is not a treatment outcome.
What the human studies measured
Swipe to see all columns
| Study / population | Finding | What it does not prove |
|---|---|---|
| Acute hormone comparison: 6 young and 6 elderly subjects[1] | GH rose alongside prolactin, ACTH and cortisol | No long-term muscle, fat or function endpoint |
| Randomized crossover: n = 7 healthy lean men; subcutaneous infusion[4] | Meal intake 9,409 vs 7,118 kJ; +35.9% with GHRP-2 | One laboratory meal does not establish chronic weight change |
| Repeated subcutaneous injections: n = 9 healthy subjects, 5 days[5] | GH response attenuated; IGF-1 did not increase | Too small and short to establish a long-term benefit or harm |
How GHRP-2 differs from other secretagogues
GHRP-2 activates the growth-hormone secretagogue receptor, also called the ghrelin receptor. GHRH analogs stimulate a separate pathway. Both can affect GH release, but a shared hormone endpoint does not make them interchangeable. Our growth-hormone secretagogue overview explains the difference between the families. The GHRP-6 evidence review covers a related peptide.
Why a GH pulse does not establish muscle gain
Acute stimulation studies show that the pituitary can release GH after exposure. Diagnostic testing uses that response to investigate hormone deficiency; it does not demonstrate that repeated exposure improves a healthy adult’s strength, body composition or lifespan.[3]Older adults with reduced GH secretion have also been studied, including repeated exposure and IGF-1 responses.[2] Those participants should not be relabeled as all having diagnosed GH deficiency, or their findings transferred to healthy athletes.
The five-day experiment is informative but narrow: diminished GH responses and unchanged IGF-1 occurred under that particular regimen.[5] It does not establish that every schedule causes the same response, and it supplies no reason to escalate or combine unapproved peptides. Likewise, increased appetite in the seven-person crossover is a measured short-term effect, not evidence that GHRP-2 will cause a particular amount of weight gain.[4]
Approval, compounding and online products
GHRP-2 is not an FDA-approved treatment for fat loss, muscle building or anti-aging. FDA’s compound-specific safety assessment covers injectable and nasal administration.[6]A prescription or a “research use” label does not establish an online product’s identity, sterility, effectiveness or approval. The peptide access guide explains why drug approval and compounding rules require separate checks.
What to take from the evidence
GHRP-2 has demonstrated endocrine activity. Evidence for a useful chronic treatment is a different question, and the studies summarized here do not answer it for muscle gain, fat loss or longevity. Endocrine symptoms deserve clinical assessment; this evidence review does not supply a self-use protocol. Sermorelin, a GHRH analog that pharmacies can still compound, is the prescription route most telehealth services offer; the Lttl review shows its full price ladder, from $149 for four weeks.