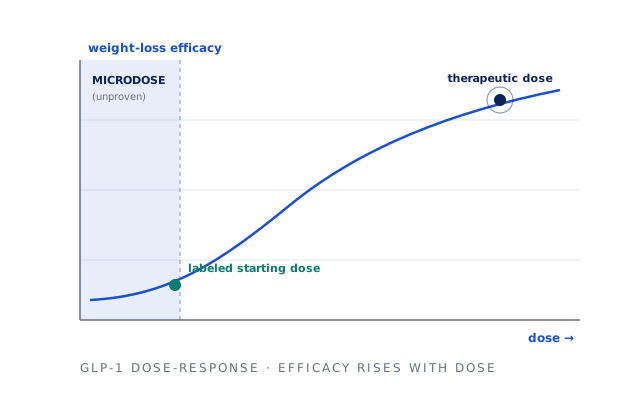
GLP-1 “microdosing” has no standard clinical definition. It usually means using less than a labeled dose, remaining at an initiation dose, or stretching the interval. Completed randomized evidence establishing a specific microdosing weight-loss or maintenance protocol was not identified in this review. Lower approved maintenance doses and clinician-directed slower titration are different decisions. The Belle review covers a flat $199 monthly semaglutide price that stays the same at every dose.
Which evidence is relevant?
Swipe to see all columns
| Evidence | What was studied | What it can tell you |
|---|---|---|
| Semaglutide dose-ranging trial: 957 adults with obesity, without diabetes[1] | Daily subcutaneous injections for 52 weeks; 0.05 mg group −6.0%, 0.4 mg group −13.8%, placebo −2.3% weight | A dose response under a specific daily regimen; not validation of weekly microdosing |
| SURMOUNT-4: 670 randomized adults without diabetes[6] | After a 36-week lead-in, continue maximum tolerated tirzepatide 10/15 mg or switch to placebo for 52 weeks | Continuation −5.5% vs withdrawal +14.0% from randomization; no reduced-dose arm |
| Diabetes Care clinical letter, 2025[9] | Discussion of individualized semaglutide multidose-pen use | An off-label clinical proposal, not a controlled outcomes trial |
What does the low-dose semaglutide trial actually show?
The 2018 trial used once-daily injections and lifestyle counseling. Its lowest semaglutide group lost more weight than placebo, but that result cannot be relabeled as evidence for taking the same amount once weekly. The primary analysis included randomized participants and imputed missing data; it was not a report limited to successful completers.[1]Neither this trial nor the pivotal semaglutide trials establishes longevity or cardiovascular benefits for an untested microdose.
Starting dose, slower titration and maintenance are different
Labels use initiation schedules to improve tolerability. Zepbound’s initiation dose is not an approved maintenance dose, while its weight-management label permits more than one maintenance dose selected by response and tolerability.[5] The Wegovy injection schedule similarly distinguishes escalation from maintenance.[4] A lower approved dose should not be described as ineffective simply because a higher dose exists. Our maintenance-dose guide explains those distinctions by product.
Can microdosing maintain weight already lost?
SURMOUNT-4 shows substantial regain after withdrawal in participants who completed a tirzepatide lead-in. It does not determine the minimum effective maintenance dose, prove that every lower dose fails, or predict an individual’s response.[6] A 2025 clinical letter discusses individualized dosing in diabetes care and explicitly acknowledges limited supporting evidence; that discussion should not be presented as a randomized trial.[9]
Compounded products add a separate uncertainty
Microdosing is discussed for both approved multidose devices and compounded vials. Compounded drugs do not become FDA-approved because the prescription uses a small dose. FDA’s GLP-1 compounding position and product-quality concerns must be considered separately from efficacy.[7]See the compounded versus branded GLP-1 guide for that distinction. Fewer side effects, lower total cost and reliable maintenance at an untested regimen are possibilities to investigate, not established guarantees.