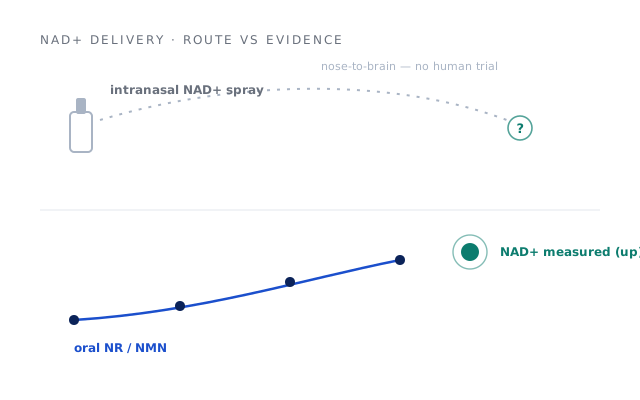
No human trial shows that an NAD⁺ nasal spray raises NAD⁺ in your blood or brain. The only published intranasal NAD⁺ study is in mice and lab-grown nasal cells. Oral precursors are better supported: in the first human dosing study, single 100, 300 and 1,000 mg doses of nicotinamide riboside raised blood NAD⁺ metabolites in a dose-dependent way.
“NAD⁺ nasal spray” is one of the newer entries in the NAD⁺ marketplace: a bottle you spritz into each nostril, sold on the premise that intranasal delivery is a faster, needle-free way to “boost NAD⁺.” The pitch borrows all the excitement built up around NAD⁺ biology and staples it to a convenient format. The problem is that convenience and evidence are two different things — and of the delivery routes people actually buy, the nasal one has by far the least direct human data behind it.
What it actually is
A NAD⁺ nasal spray is a liquid containing either NAD⁺ itself or an NAD⁺ precursor, formulated for intranasal administration. The marketing logic runs in two directions at once: that spraying it into the nose lets NAD⁺ enter the bloodstream while bypassing the gut, and — more ambitiously — that the nasal passage offers a direct “nose-to-brain” shortcut that could raise NAD⁺ in the central nervous system. Both are delivery-format claims. Neither is a claim about NAD⁺ biology, which is a separate and much better-studied question covered in our review of NAD⁺ precursors (NR and NMN).
The delivery question: does spraying it actually do anything?
This is where the format falls down. NAD⁺ is a large, charged, water-soluble molecule — exactly the kind of compound that does not cross mucosal membranes easily. For intranasal delivery to work, a specific formulation has to be engineered and then validated to show it reaches the target, and that validation is highly molecule- and formulation-dependent rather than automatic.[4] The honest state of the evidence for the NAD⁺ spray specifically: there is essentially no controlled human trial showing that intranasal NAD⁺ raises systemic NAD⁺, let alone brain NAD⁺, in people. The theoretical nose-to-brain route is genuinely interesting, but for this molecule it is unproven — an idea, not a result.
The closest thing to evidence is a 2026 lab study: intranasal NAD⁺ helped regrow smell-sensing nerve cells in mice whose sense of smell had been chemically destroyed, and pushed cultured human nasal stem cells toward becoming those neurons.[5] That is a local effect on the lining of the nose, in animals. It did not measure NAD⁺ in blood or brain, and it says nothing about a consumer spray in people.
What we do know: the oral precursors
The contrast with oral precursors is stark, and it is the reason this article exists. The first human pharmacokinetic study of oral nicotinamide riboside (NR) gave single doses of 100, 300 and 1,000 mg and found dose-dependent rises in the blood NAD⁺ metabolome: the precursor is absorbed and converted as the biochemistry predicts.[1] A separate randomized, double-blind, placebo-controlled crossover trial (two 6-week periods) in healthy middle-aged and older adults found chronic NR was well tolerated and raised NAD⁺ metabolism in blood.[2] And NMN's most-cited trial, a 10-week randomized, double-blind trial in overweight or obese postmenopausal women with prediabetes, reported improved skeletal-muscle insulin sensitivity: a small, surrogate-endpoint result, but a real one.[3]
Read that carefully: the oral data establish that the compound gets in and that the biomarker moves. That is precisely the step the nasal format has never demonstrated. When a spray borrows the credibility of the NAD⁺ story, it is borrowing evidence that belongs to a different delivery route.
How the formats stack up
Among the routes people actually buy, there is a rough hierarchy of directness of evidence. Oral NR/NMN has the most human data for raising measured NAD⁺. NAD⁺ IV therapy delivers the molecule straight into the bloodstream, so systemic exposure is not in doubt, though controlled outcome data remain thin. Subcutaneous NAD⁺ injections occupy a middle ground with even less formal study. The nasal spray sits at the bottom of that list for direct evidence: it is the one format where even the basic “does it reach the bloodstream in humans” question lacks a controlled answer. If you want to compare routes side by side, our NAD⁺ format comparator lays out the trade-offs, and the cost of NAD⁺ therapy varies widely by format too.
The Embody review separates the advertised introductory and renewal NAD⁺ prices for the spray and injection. When comparing those prices, ask how much each order supplies. A matching monthly price tells you nothing about how much NAD⁺ reaches the bloodstream.
The honest bottom line
A NAD⁺ nasal spray is a convenient, needle-free, heavily marketed format riding on genuine excitement about NAD⁺ biology — but it carries the least direct evidence of the common delivery routes. What is supported by human data is narrow and specific: oral precursors are absorbed and raise the NAD⁺ biomarker. What is not supported is that spraying NAD⁺ into your nose raises systemic or brain NAD⁺ at all, and — as with every NAD⁺ format — no route has been shown to slow aging, prevent disease, or deliver a clinical benefit in people. If you are drawn to the spray for convenience, buy it knowing you are paying for a format whose core delivery claim has not been tested, not for a proven result.