Retatrutide has produced the largest weight-loss numbers yet reported for a drug — the efficacy side is laid out in our clinical evidence monograph. This page is the other half of that ledger: what the same trials reported about harm. The honest framing first — retatrutide is investigational, still in Phase 3, and the historical table below describes Phase 2, with a separate published Phase 3 update. It is a real drug with a real, dose-related side-effect profile, not a benign peptide.
The dominant signal: gastrointestinal events
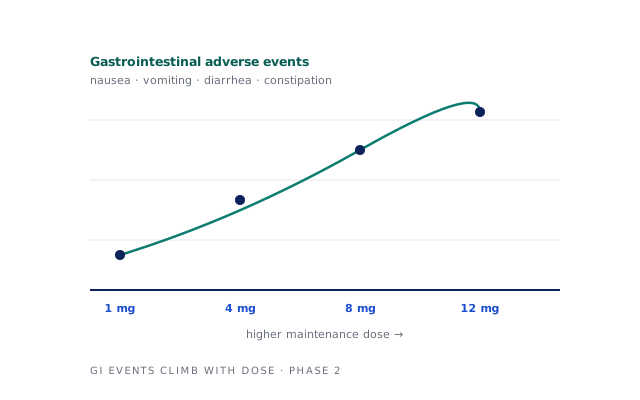
Like every incretin-based agent, retatrutide’s most common adverse effects were gastrointestinal. In the 48-week Phase 2 obesity trial, nausea, diarrhea, vomiting and constipation were the most frequently reported events, they were mostly mild to moderate, and they were dose-related — more common at the higher maintenance doses and concentrated during the dose-escalation period.[1] The parallel Phase 2 trial in adults with type 2 diabetes put numbers on the same pattern: mild-to-moderate gastrointestinal events in 67 of 190 participants on retatrutide (35%) against 6 of 45 on placebo (13%), climbing with dose from 13% in the 0.5 mg group to 50% in the fastest 8 mg escalation arm.[2] This is why escalation schedule matters, and it is covered in our dosage page and in the broader GLP-1 GI side-effect timeline.
Swipe to see all columns
| Adverse effect | What the Phase 2 trials found | Trial |
|---|---|---|
| Nausea | Most common; mild–moderate; dose-related | Obesity + T2D |
| Diarrhea | Common; dose-related | Obesity + T2D |
| Vomiting | Common; more frequent at higher doses | Obesity + T2D |
| Constipation | Reported among the leading GI events | Obesity |
| Heart-rate increase | Dose-dependent; peaked ≈ week 24, then declined | Obesity |
The glucagon consideration: heart rate
The third receptor is what sets retatrutide apart, and it carries its own signal. In the obesity trial, mean heart rate rose in a dose-dependent way, peaked at around week 24, and then declined toward week 48 — a transient pattern rather than a steady climb.[1] Glucagon-receptor agonism raising heart rate is mechanistically expected, and it is precisely the kind of cardiometabolic effect that a mid-stage trial can describe but cannot adjudicate for long-term safety.
What we simply don’t know yet
The largest caveat is limited long-term exposure and outcomes evidence. There are no multi-year exposure results, no completed cardiovascular or renal outcomes results established here, and no post-marketing surveillance — because there is no market. The detailed adverse-event tables on this page are still a Phase 2 read-out, while published Phase 3 adds a larger study population. Rare or delayed adverse effects, by definition, do not show up reliably in trials of this size and duration; that is what the completed Phase 3 program and any eventual FDA review exist to establish. How retatrutide’s tolerability is likely to compare against the approved dual agonist is discussed in our retatrutide versus tirzepatide comparison — but even there, cross-trial safety comparisons are suggestive, not definitive.
The gray-market problem sits on top of all of this
Because retatrutide is not approved, supply requires a clinical trial or an authorized access pathway. Anything sold as “research” retatrutide is unregulated, and it adds a second layer of risk that has nothing to do with the molecule’s own adverse events: unknown purity, possible contamination, and unverifiable dosing. The trial data above describe a specific compound given at controlled doses under medical supervision. None of those conditions hold for material bought online, so the Phase 2 safety profile cannot be assumed to transfer to it. This page is not a self-use guide.
The honest bottom line
Retatrutide’s side-effect story is, so far, a familiar incretin one told at a new intensity: dose-related gastrointestinal events as the dominant burden, plus a transient glucagon-linked rise in heart rate.[1][2] None of that is disqualifying — it is roughly what the class predicts — and the drug remains investigational. There is no long-term safety record, no approved product, and no approved retail product. The appropriate posture is to watch the Phase 3 data as it arrives and to treat any decision as one for a clinician, not a forum. Until it reaches US pharmacies, the weight-loss drugs you can actually be prescribed are semaglutide and tirzepatide; the Eden review covers a service offering both compounded and branded versions.