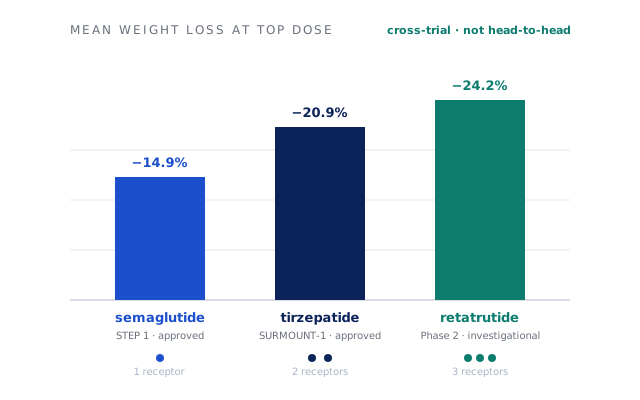
Semaglutide, tirzepatide and retatrutide activate different combinations of metabolic receptors. That helps explain their mechanisms, but receptor count does not rank treatments. Semaglutide and tirzepatide have approved uses; retatrutide now has published Phase 3 evidence and remains investigational. Compare the trial populations and analysis methods alongside each percentage.
The mechanism ladder, rung by rung
The three agents differ by how many incretin-and-metabolic receptors a single peptide activates. Semaglutide is a GLP-1 receptor mono-agonist: one pathway, driving appetite suppression and insulin secretion. Tirzepatide adds the GIP receptor, making it a dual agonist — the extra incretin arm is the mechanistic reason many expected it to outperform semaglutide, a question taken up in our tirzepatide vs semaglutide review. Retatrutide adds a third target, the glucagon receptor, which is thought to raise energy expenditure and mobilize hepatic fat on top of the two incretin effects. Each added rung is a plausible reason to expect more weight loss — but mechanism predicts the direction of an effect, not its size.
The three headline numbers
In STEP 1, once-weekly semaglutide 2.4 mg produced a mean weight loss of about 14.9% at 68 weeks in adults with obesity and without diabetes.[1] In SURMOUNT-1, tirzepatide at 15 mg reached roughly 20.9% at 72 weeks in a comparable population.[2] In the retatrutide Phase 2 obesity trial, 338 adults received the triple agonist or placebo, and the 12 mg dose produced about 24.2% mean weight loss at 48 weeks.[3] The ordering matches the mechanism ladder exactly — which is satisfying, and also the reason to be careful. A neat pattern is easy to over-read.
Why this is not a fair three-way race
Those three figures come from three different studies, run in different people, over different durations, at different phases of development. STEP 1 ran 68 weeks; SURMOUNT-1 ran 72; the retatrutide trial ran 48 and, notably, had not clearly plateaued when it ended — a detail we unpack in the retatrutide clinical evidence review. Baseline weights, trial designs and dropout handling all differ. Lining the bars up side by side suggests the ranking is right; it does not prove the magnitudes are directly comparable.
TRIUMPH-1 is now published: its 80-week treatment-regimen estimate at 12 mg was −25.0% versus −3.9% with placebo.[6] This analysis differs from efficacy-estimand sponsor headlines. TRIUMPH-5 has completed enrollment, but the sources checked do not establish completed comparison results.[8] Until then, separate-trial percentages cannot prove superiority for an individual patient.
The three-way at a glance
Swipe to see all columns
| Semaglutide | Tirzepatide | Retatrutide | |
|---|---|---|---|
| Mechanism | GLP-1 (mono-agonist) | GIP + GLP-1 (dual) | GIP + GLP-1 + glucagon (triple) |
| Receptors targeted | 1 | 2 | 3 |
| Headline weight loss | ≈ 14.9% (STEP 1) | ≈ 20.9% (SURMOUNT-1) | ≈ 24.2% in historical Phase 2; see published Phase 3 update |
| Trial phase & length | Phase 3 · 68 wk | Phase 3 · 72 wk | Phase 2 (48 wk, n=338); published Phase 3 also available |
| Regulatory status | FDA-approved | FDA-approved | Investigational — not approved |
| Dosing route | Once-weekly injectable | Once-weekly injectable | Once-weekly injectable |
| Available now? | Yes | Yes | No |
What the drugs share
For all their differences, the three have a family resemblance. All are once-weekly subcutaneous injectables, and all share the incretin-class tolerability profile: nausea, vomiting and diarrhea that are common, dose-related and typically managed by slow dose escalation. The one head-to-head fact anywhere in this trio is between the two approved drugs — SURMOUNT-5 randomized tirzepatide against semaglutide at obesity doses and found tirzepatide produced greater weight loss.[4] TRIUMPH-5 compares retatrutide with tirzepatide, but no completed results were established in this check, which is exactly why the retatrutide vs tirzepatide comparison stays cross-trial. Until it reaches US pharmacies, the weight-loss drugs you can actually be prescribed are semaglutide and tirzepatide; the Belle review covers a flat monthly price that stays the same at every dose.
The honest bottom line
The mechanism comparison is useful; a clinical ranking requires stronger evidence. Retatrutide’s published Phase 3 results extend its early record, but separate trials cannot settle superiority. Semaglutide and tirzepatide have approved treatment pathways. The right choice also depends on indication, contraindications, tolerability, access and a clinician’s assessment.