The peptide a U.S. clinician can most readily prescribe for a body-composition goal is compounded sermorelin, about $150–$250 a month as of October 2026. Tesamorelin is FDA-approved as Egrifta, but only for HIV-related belly fat. Neither is approved to build muscle, and ipamorelin, CJC-1295, BPC-157, TB-500 and MK-677 have no lawful compounding route today.
This is the practical guide: what you can actually get prescribed, roughly what it costs, and where each compound stands with the FDA and WADA. For the trial-by-trial read of whether any of these build muscle, see our evidence explainer, peptides for muscle growth: what the evidence shows for each one.
Which peptides for muscle growth can you get prescribed?
Swipe to see all columns
| Compound | Can a U.S. pharmacy fill it? | Typical cost | FDA status | WADA |
|---|---|---|---|---|
| Sermorelin | Yes, compounded on a prescription | ~$150–$250/mo via telehealth | No FDA-approved product on the market (the original brand was discontinued) | Prohibited (S2) |
| Tesamorelin | Brand Egrifta, yes; compounded copies are on weak legal ground (a biologic, outside the compounding exemptions) | Compounded from ~$300/mo; brand usually through insurance | FDA-approved only to reduce excess abdominal fat in HIV | Prohibited (S2) |
| Ipamorelin | No lawful compounding route from bulk powder | — | Not approved; on the FDA’s significant-safety-risk list for outsourcing facilities | Prohibited (S2) |
| CJC-1295 | No lawful compounding route from bulk powder | — | Not approved; compounding nomination withdrawn | Prohibited (S2) |
| MK-677 / ibutamoren (not a peptide) | No | — | Not approved; on the FDA’s significant-safety-risk list | Prohibited (S2) |
| BPC-157 | No, pending any FDA action | — | Not approved; nomination withdrawn; July 2026 advisory vote 8–6 to recommend, non-binding | Prohibited (S0) |
| TB-500 | No, pending any FDA action | — | Not approved; nomination withdrawn; July 2026 advisory vote 8–6 to recommend, non-binding | Prohibited (S2) |
| IGF-1 LR3, follistatin | No | — | Not approved; research-chemical only | Prohibited (S2) |
| Testosterone (not a peptide) | Yes, for diagnosed low testosterone | See TRT cost guide | FDA-approved for hypogonadism; Schedule III controlled substance | Prohibited (S1) |
Prices move, so check the current ranges in our sermorelin cost, tesamorelin cost and peptide therapy cost guides. For testosterone, which has far stronger muscle data than any peptide but is a controlled hormone with its own risks, see the TRT cost guide.
Where can you buy peptides for muscle growth?
Lawfully, only through a licensed prescriber and a licensed pharmacy: a state-licensed compounding pharmacy or an FDA-registered outsourcing facility for compounded sermorelin, or a specialty pharmacy for brand Egrifta (tesamorelin), which the FDA regulates as a biologic outside the compounding exemptions.[12] Telehealth services handle the prescribing step online and ship from a partner pharmacy. Sites selling vials “for research use only, not for human consumption” are not selling medicine for people, whatever the checkout page implies, and nobody verifies what is in the vial. Our peptide therapy provider comparison lists telehealth services by care model and price, and where to get peptides safely covers how to check the pharmacy behind any prescription.
Are peptides for muscle growth legal?
It depends on the compound. Sermorelin can be prescribed and compounded, and brand tesamorelin (Egrifta) can be prescribed, on label or off. For the rest, the deciding fact is the FDA’s compounding review. BPC-157, TB-500, CJC-1295, ipamorelin (for 503A pharmacies), GHK-Cu and others were nominated for the list of bulk substances pharmacies may compound with, the nominations were withdrawn, and in April 2026 the FDA moved them off its Category 2 significant-safety-risk list into a “nominated but withdrawn” list. That is not a clearance: a substance has to be added to the bulks list before a pharmacy may compound it. Ibutamoren (MK-677) remains in Category 2 for both pharmacy types, and ipamorelin remains there for outsourcing facilities.[8] In July 2026 the FDA’s Pharmacy Compounding Advisory Committee voted 8–6, with one abstention, to recommend adding BPC-157 and TB-500 to the list; the FDA’s own staff had recommended against it, the vote is advisory, and the FDA must still act before anything changes.[9][11] Our are peptides legal? guide walks through the full map.
Are muscle peptides banned in sport?
Yes, all of them, at all times. The WADA Prohibited List bans GHRH analogs such as sermorelin and tesamorelin, growth-hormone secretagogues such as ipamorelin and ibutamoren, and growth factors including thymosin-β4 fragments like TB-500 under S2, and catches unapproved substances such as BPC-157 under S0.[10] If you are tested, a prescription does not change that without a therapeutic use exemption; see banned peptides and WADA.
Which of them has the best evidence for muscle?
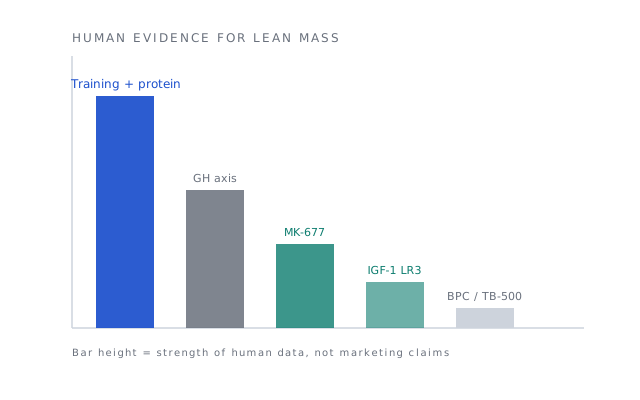
None has good evidence for building muscle in healthy adults; the full ranking is in the evidence explainer. The short version for the two you can get prescribed: sermorelin and tesamorelin prompt the pituitary to release more of your own growth hormone, which raises IGF-1. In a retrospective review of 14 men on thrice-daily GH-releasing peptide therapy for a mean of 134 days, IGF-1 rose from 159.5 to 239.0 ng/mL.[2] Tesamorelin is the only one with large placebo-controlled trials, and those were run in people with HIV and excess belly fat: pooled phase 3 data showed tesamorelin cut visceral fat by a treatment effect of 15.4% against placebo at 26 weeks,[3] with the clearest responses in patients who had higher baseline IGF-1 and triglycerides.[4] Those trials did not show a durable gain in lean mass or measured strength.
MK-677: one good trial, telling result
MK-677 is an orally active ghrelin-mimetic that raises GH and IGF-1 without an injection, which is why bodybuilding forums treat it as a near-anabolic. It does have a clean piece of evidence: a randomized trial in healthy older adults (n = 65) found that MK-677 increased fat-free mass by 1.1 kg over a year, against a 0.5 kg fall on placebo.[1] Read the fine print, though. The trial found no gain in muscle strength or function, and side effects included rising fasting glucose, mild leg swelling and muscle pain. It is the best single result in the muscle-peptide space — and it still falls short of “builds muscle that performs.”
BPC-157, TB-500 and IGF-1 LR3
These are the names that fill muscle-stack forums, and they are the ones you cannot get lawfully compounded. BPC-157 raised growth-hormone receptor expression in tendon cells in a dish,[5] and thymosin β-4, the parent molecule of TB-500, has documented roles in blood-vessel growth and tissue repair,[6] but no controlled human trial shows either one speeds recovery or adds muscle. IGF-1 LR3 has no human trials for muscle at all.