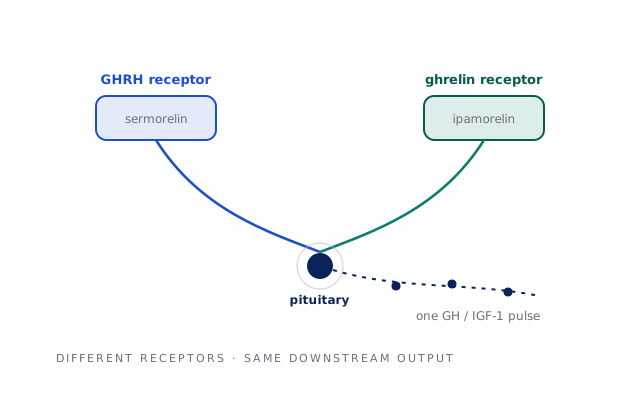
Both raise your own growth hormone, through different receptors. Sermorelin copies the brain’s GHRH signal and has a documented pediatric growth-hormone-deficiency record; ipamorelin mimics ghrelin and is known for selectivity in animal studies. Neither has outcome trials in healthy adults, and ipamorelin is not cleared for pharmacy compounding.[1][2][6]
“Ipamorelin vs sermorelin” usually gets answered with vibes — one is “gentler,” the other is “more natural” — and almost never with the one fact that actually separates them. They are both growth-hormone–axis peptides, and both finish at the same biological event: a pulse of your own growth hormone released from the pituitary. But they get there through two different receptors, and that single difference drives everything downstream — the selectivity profile, why one is stacked and the other isn’t, and which goal each one suits. Get the receptor story right and the rest of the comparison falls out of it.
GHRH-R
Sermorelin's target — the growth-hormone-releasing-hormone receptor
Ghrelin-R
Ipamorelin's target — the GH secretagogue (ghrelin) receptor
1 pulse
Both converge on the same endogenous GH/IGF-1 output
The fork in the road: two receptors, not one drug class
The pituitary cells that release growth hormone — the somatotrophs — carry more than one “go” button. Sermorelin presses the first one. It is a synthetic copy of the first 29 amino acids of growth-hormone-releasing hormone, the brain’s own GH command, and it binds the GHRH receptor.[1] So sermorelin essentially impersonates the hypothalamic signal your body already uses, asking the pituitary to fire in its natural, pulsatile rhythm.
Ipamorelin presses a different button. It is not a GHRH copy at all; it is a small synthetic peptide that mimics ghrelin — the “hunger hormone” — and binds the growth hormone secretagogue receptor (the ghrelin receptor) on those same somatotrophs.[2] Two molecules, two receptors, one downstream output. That is why lumping them into a single “GH peptide” bucket misleads: a GHRH analog and a ghrelin mimetic are pharmacologically as different as a thermostat and a space heater — both can warm the room, by entirely separate means.
Selectivity: ipamorelin’s actual headline feature
The thing ipamorelin is genuinely known for isn’t raw strength — it’s a clean signal. Older ghrelin-type secretagogues tended to drag other hormones up with the GH pulse, spiking cortisol (the stress hormone) and prolactin. The foundational pharmacology that introduced ipamorelin described it as the first selective GH secretagogue precisely because it triggered GH release with little of that off-target cortisol and ACTH spillover: in pigs, GHRP-6 and GHRP-2 raised ACTH and cortisol while ipamorelin did not, even at more than 200 times its effective GH dose.[2] That selectivity is the property the modern peptide market keeps selling under words like “gentle” or “clean.”
Sermorelin’s selectivity comes from a different place: it works through the body’s own GHRH pathway and its negative-feedback brakes, so the GH it elicits stays roughly within physiologic, pulsatile bounds rather than being force-fed. So both are described as “physiologic,” but for non-overlapping reasons — sermorelin because it borrows the native release circuit, ipamorelin because it avoids the collateral hormone spikes of its own drug class.
How they’re actually used: solo vs stacked
Here’s a practical fact that surprises people: you rarely see ipamorelin used alone. The standard configuration is ipamorelin plus CJC-1295, a long-acting GHRH analog. The logic is exactly the receptor story above — CJC-1295 covers the GHRH-receptor lever (with a half-life long enough to provide a sustained background), while ipamorelin adds the ghrelin-receptor lever on top, and randomized human trials of CJC-1295 alone confirmed that GHRH-analog dosing produces real, multi-day elevations in GH and IGF-1.[3] We cover that combination on its own terms in the ipamorelin & CJC-1295 evidence review.
Sermorelin, by contrast, is typically run solo. Since it already acts on the GHRH receptor, bolting on CJC-1295 would mostly be hitting the same lever twice; the more common pairing question for sermorelin is whether to add a ghrelin-mimetic at all. In other words, the “ipamorelin vs sermorelin” framing is slightly off from how the market really behaves: it’s usually sermorelin solo vs an ipamorelin-containing stack. The deeper monograph on the GHRH side is our sermorelin evidence review.
Evidence tier: where each one actually has data
Neither peptide is an FDA-approved finished product for the longevity uses they’re marketed for, but the shape of their evidence differs. Sermorelin has the more conventional clinical pedigree: it was used to diagnose growth-hormone deficiency in children and, at 30 µg/kg once daily, to treat some prepubertal children with it, with sustained gains in height velocity over 12 months, though less than with recombinant GH.[1] Ipamorelin’s evidence is heaviest on the pharmacology (the selective-secretagogue work in rats and pigs), and its one randomized patient trial, for gut recovery after bowel surgery (n = 114), found no significant benefit over placebo.[7] On IGF-1 in adults, the human data are thin: a retrospective review of 14 men on testosterone taking sermorelin with GHRP-2 and GHRP-6 (not ipamorelin) three times daily saw IGF-1 rise from 159.5 to 239.0 ng/mL (p < 0.0001).[4] That is a surrogate biomarker, not a hard outcome, and it’s the honest ceiling for both. Both also sit a full weight class below injected recombinant growth hormone, which supplies the hormone from outside rather than asking the pituitary for it — the split we unpack in ipamorelin versus HGH, where the potency gap and the risk profile both follow from that difference.
Swipe to see all columns
| Attribute | Sermorelin | Ipamorelin |
|---|---|---|
| Receptor target | GHRH receptor (the brain's own GH-release signal) | Ghrelin / GH-secretagogue receptor |
| Mechanism | GHRH analog — mimics growth-hormone-releasing hormone | Ghrelin mimetic — imitates the gut hormone ghrelin |
| Selectivity | Physiologic via native feedback loops | Selective for GH; no ACTH/cortisol rise in pigs |
| Typical use pattern | Usually run solo | Usually paired with CJC-1295 (a GHRH analog) |
| Evidence tier | Pediatric GH-deficiency diagnosis and treatment | Animal pharmacology; one negative phase 2 trial (post-surgical gut) |
| FDA compounding status (Oct 2026) | Not on FDA's Category 2 safety-risk list | Not cleared for 503A pharmacies; Category 2 for 503B |
| Hard longevity outcomes | None in healthy adults | None in healthy adults |
Side effects flow from the mechanism
The safety contrasts aren’t arbitrary — they trace back to the receptor each peptide hits. Because ipamorelin engages the ghrelin receptor, the effects to expect are the ones in ghrelin’s own wheelhouse, such as increased appetite (repeated doses raised food intake in rats after surgery).[8] In its surgical trial it was well tolerated over up to 7 days of intravenous dosing,[7] but the FDA notes a published report of serious adverse events, including death, with intravenous ipamorelin and keeps it on its compounding safety-risk list.[6] In the pediatric record, sermorelin’s most common adverse events were transient facial flushing and injection-site pain,[1] with any systemic effects being the predictable consequences of nudging the GH axis. Both share the deeper caveat of any GH/IGF-1 strategy: chronically pushing this pathway carries the long-standing theoretical concerns tied to IGF-1 and tissue growth, which no long-term controlled trial of either peptide has resolved.
Which fits which goal — an honest verdict
Match the peptide to the question, not to a leaderboard. If the appeal is a single, prescribable molecule with the most conventional clinical pedigree and a “work with my own rhythm” rationale, sermorelin solo is the more straightforward GHRH-receptor play. If the goal is a stronger, more synergistic GH pulse and the user is already thinking in terms of a stack, ipamorelin — paired with CJC-1295 — is the ghrelin-receptor lever that’s built to be combined, with selectivity as its distinguishing virtue. What neither answer changes is the ceiling: both move a biomarker, neither has hard-outcome longevity data in healthy adults, and both are sold largely outside the approved-drug system. To sit the broader peptide field side by side on evidence grade, use our peptide evidence matrix, and for the adjacent oral secretagogue comparison see MK-677 vs sermorelin. For the other GHRH cross-shop, the tesamorelin vs sermorelin breakdown covers the approved end of the spectrum.
Cost and where to start
Price tracks the use pattern, not the molecule. A solo GHRH analog and a two-peptide stack are different line items: see the sermorelin cost breakdown for the solo route and the CJC-1295 & ipamorelin cost guide for the stacked one. If you’re weighing a provider rather than a molecule, our peptide therapy provider comparison ranks the legitimate telehealth options on price and care model — the safer starting point than a gray-market vial of either peptide.
The honest bottom line
Sermorelin and ipamorelin aren’t rivals so much as two different keys to the same lock. Sermorelin works the GHRH receptor — the brain’s native release signal — and is typically used alone; ipamorelin works the ghrelin receptor with notable selectivity and is typically stacked with CJC-1295 to hit both levers at once. Both reliably raise GH and IGF-1, and there the evidence stops: neither has demonstrated, in controlled trials of healthy adults, that the biomarker bump becomes muscle, longevity, or reversed aging. So “which is better” resolves to which lever fits your goal — with the shared, unglamorous truth that both are biomarker stories standing in for outcomes that haven’t been proven. Widen the comparison to include the one compound in this family with phase 3 data behind it in sermorelin vs ipamorelin vs tesamorelin.