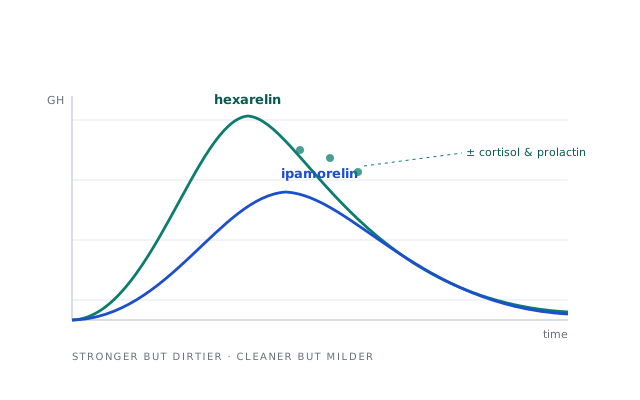
Hexarelin is the stronger growth-hormone releaser; ipamorelin is the cleaner one. A bolus of hexarelin raises prolactin, ACTH and cortisol along with GH, and over 16 weeks of twice-daily use its GH response fell by about 45%. Ipamorelin left ACTH and cortisol alone even at 200 times its effective dose, but only in animal studies. Neither is FDA-approved.[3][2][1]
Put hexarelin and ipamorelin next to each other and you are not comparing two different ideas — you are comparing two members of the same family arguing over the same job. Both are growth-hormone-releasing peptides (GHRPs): small synthetic molecules that switch on growth-hormone output by binding the ghrelin receptor, the GH-secretagogue receptor, on the pituitary’s somatotroph cells.[4] So the question is never “which mechanism” — it is the same mechanism — but rather how cleanly each one does it. And on that axis the two peptides land in opposite corners: one trades strength for messiness, the other trades a little strength for a clean signal.
Same receptor
Both are GHRPs acting at the ghrelin / GH-secretagogue receptor
More potent
Hexarelin — but with cortisol & prolactin spillover
More selective
Ipamorelin — minimal off-target hormone effects
Same family, same receptor
Before the contrast, the common ground. Hexarelin is a hexapeptide and ipamorelin a pentapeptide, but both belong to the GHRP class that emerged from medicinal-chemistry work on growth-hormone secretagogues, and both stimulate GH through the ghrelin-type receptor rather than the separate GHRH receptor that peptides like sermorelin and CJC-1295 hit.[4] In other words, this is an intra-class face-off. If you have already read our ipamorelin vs sermorelin breakdown, this is the other side of that coin: there the split was GHRH-receptor versus ghrelin-receptor; here both peptides sit on the ghrelin-receptor side, and the differences are about quality and durability of the signal, not the lever pulled.
Potency: hexarelin hits harder
On raw GH-releasing power, hexarelin is the heavier hitter. It is repeatedly described in the human literature as a powerful GH-releasing peptide capable of provoking a marked GH surge across oral, intranasal, intravenous and subcutaneous routes.[2] Within the broader GHRP family, hexarelin sits at the strong end of the potency spectrum, which is exactly why it drew so much early clinical interest as a possible GH stimulus.[4] Ipamorelin, by design, was tuned for a different goal — the foundational work reported its GH-releasing potency as comparable to the older GHRP-6 rather than chasing a record-high peak.[1] So if the only question were “which produces the bigger acute GH spike,” hexarelin would generally win. But that is rarely the only question that matters.
Selectivity: ipamorelin’s whole reason to exist
Here is where the two peptides diverge most sharply. Older, more potent GHRPs do not confine themselves to growth hormone; they tend to drag the stress-axis hormones up at the same time. The pharmacology that introduced ipamorelin made this explicit: in swine, the established GHRPs it was benchmarked against raised plasma ACTH and cortisol, whereas ipamorelin did not raise ACTH or cortisol to a degree different from a clean GHRH stimulus — and held that clean profile at doses more than 200-fold above the ED50for GH release — which is what earned it the “first selective growth-hormone secretagogue” label.[1] That selectivity is the single property the modern peptide market keeps re-selling under words like “clean” and “gentle.”
Hexarelin sits on the messier side of that line, with one nuance. In a randomized study in six healthy young men, an intravenous hexarelin challenge produced significant rises not just in GH but in prolactin, ACTH and cortisol as well. Yet two or three small subcutaneous doses a day (1.5 µg/kg) raised 24-hour GH without changing prolactin, ACTH or cortisol secretion.[3] So the off-target hormone traffic that ipamorelin was engineered to avoid is clearest with a large, fast dose of hexarelin; at small subcutaneous doses, the difference is narrower than the “dirty” reputation suggests.
Desensitization: the strength that fades
Potency that you cannot sustain is worth less than it looks. A long-term human study of twice-daily subcutaneous hexarelin tracked the GH response over sixteen weeks and found it partially attenuated over the dosing period — the mean area under the GH curve fell from 19.1 µg/L·h at baseline to 12.3 by week four and 10.5 by week sixteen (P = 0.0003 across the study).[2] Crucially, the response climbed back to 19.4 µg/L·h four weeks after stopping, so the effect was a reversible down-regulation rather than permanent damage — but it is still a real ceiling on what continued hexarelin dosing buys you.[2] The more you press this particular button, the less the pituitary answers.
Whether ipamorelin avoids this fade is not known from human data: no long-term human study of repeated ipamorelin dosing comparable to the hexarelin one exists. A review of the GHRP class describes partial desensitization as a family trait, stronger with continuous infusion and weaker with intermittent doses.[4] The practical reading: hexarelin can out-punch ipamorelin in a single session, and its edge erodes with weeks of use; ipamorelin may fare better, but that is an assumption, not a finding.
Swipe to see all columns
| Attribute | Hexarelin | Ipamorelin |
|---|---|---|
| Class | GHRP — ghrelin / GH-secretagogue receptor agonist | GHRP — ghrelin / GH-secretagogue receptor agonist |
| GH-releasing potency | Higher — a 'powerful' GH releaser | Comparable to older GHRP-6; tuned for cleanliness, not peak |
| Cortisol / ACTH effect | Raised by an IV dose; unchanged with small subcutaneous doses | No rise above a GHRH-like stimulus (pigs) |
| Prolactin effect | Raised by an IV dose | No rise (pigs) |
| Desensitization | GH response fell about 45% over 16 weeks (reversible) | No long-term human data |
| Why people pick it | Maximum acute GH push | Clean, selective signal |
| Regulatory / sport status | Not FDA-approved; WADA-banned | Not FDA-approved; not cleared for 503A compounding; FDA 503B Category 2; WADA-banned |
Why the “clean” one won the popularity contest
On paper, the stronger peptide should have been the favorite. In practice ipamorelin became the GHRP everyone reaches for, and the reasons map directly onto the contrasts above. A user does not actually want the largest possible single GH spike if it arrives with extra cortisol and prolactin and then fades after a few weeks; they want a GH signal they can run repeatedly without dragging the stress axis along for the ride. Ipamorelin’s selectivity, and its assumed (not yet measured) resistance to fading, make it look like the better fit for that goal, and that is the whole story behind its market dominance — not that hexarelin is weak, but that hexarelin’s strength comes with strings attached.[1][3] It is also why ipamorelin, not hexarelin, is the GHRP almost always paired with a GHRH analog like CJC-1295; the deeper monograph on that pairing is our ipamorelin & CJC-1295 evidence review, and the standalone hexarelin write-up is the hexarelin evidence review.
Evidence ceiling and the honest caveats
For all the head-to-head nuance, the two peptides share the same hard limit. Neither hexarelin nor ipamorelin is an FDA-approved finished product for the longevity, body-composition or recovery uses they are marketed for; the published human work is largely short-term endocrine pharmacology, not the long, controlled outcome trials that would show a GH bump turning into something a person can feel. In the 16-week hexarelin study, IGF-1, body fat, lean mass and bone density did not change significantly.[2][4] Ipamorelin also carries an FDA compounding flag: it is in Category 2 (significant safety risks) for outsourcing facilities, and for ordinary compounding pharmacies its nomination was withdrawn, which leaves it off the list of substances they may use. FDA notes a published report of serious adverse events, including death, when ipamorelin was given intravenously for gastric motility.[5] Both also share the deeper concern of any GH-axis strategy — chronically pushing growth hormone and IGF-1 carries long-standing theoretical questions around tissue growth that no long-term trial of either peptide has resolved. And both are prohibited in sport: GHRPs sit on the World Anti-Doping Agency’s banned list, so any competitive athlete using either risks a sanction regardless of the “clean” marketing.
The honest bottom line
Hexarelin and ipamorelin are the same kind of key cut to different tolerances. Hexarelin opens the GH lock harder — a more potent releaser — but it rattles the cortisol and prolactin pins on the way through and loses bite if you keep turning it. Ipamorelin opens the same lock a little more gently but more cleanly, at least in the animal pharmacology, though no long-term human study shows how it holds up over a course. That is why the weaker peptide became the popular one. Neither, though, has earned the longevity or body-composition outcomes the marketing implies, both move biomarkers rather than proven endpoints, and both are unapproved and banned in sport — so the real choice is less “stronger versus cleaner” than “is pushing this axis at all worth it for you.” To weigh the broader peptide field on evidence grade, use our peptide evidence matrix.