HGH is growth hormone itself, injected; ipamorelin only prompts your pituitary to release its own. HGH is far stronger and better studied, and is FDA-approved for diagnosed growth-hormone deficiency and a few growth disorders. Ipamorelin has no approved use, and its only randomized trial in patients (n = 114) missed its goal. Both are banned in tested sport.
“Ipamorelin vs HGH” sounds like a dose-strength question — two ways to get the same thing, one just milder. It isn’t. They sit on opposite sides of the most important line in this whole field: one is the hormone, the other only asks your body to make the hormone. Human growth hormone is recombinant somatropin — the actual molecule, manufactured and injected. Ipamorelin is a peptide that nudges your pituitary to release its own growth hormone. Everything that follows — the potency gap, the risk profile, the legality — falls out of that single exogenous-versus-endogenous split.
Exogenous
HGH — the manufactured hormone, injected from outside
Endogenous
Ipamorelin — stimulates your own pituitary GH release
Not equal
HGH is far stronger and far better studied than the peptide
The hormone vs the messenger that asks for it
HGH is growth hormone itself. Recombinant somatropin is biosynthetic human growth hormone, identical to what the pituitary makes. Its FDA label (Humatrope is one example) covers growth-hormone deficiency in children and adults plus a short list of childhood growth conditions: Turner syndrome, idiopathic short stature, SHOX deficiency and short stature after being born small for gestational age.[1] When it’s injected, the hormone is simply there in the bloodstream — your own glands didn’t have to agree to release it.
Ipamorelin never puts growth hormone into you. It is a small selective growth-hormone secretagogue — a ghrelin-receptor agonist — that prompts the pituitary’s own cells to fire a pulse of GH.[2] The body remains the manufacturer and, crucially, keeps a vote: somatostatin and negative feedback can still throttle the response. With injected HGH there is no such vote, because the gland was bypassed entirely. That is the difference between turning up a thermostat and carrying in a space heater.
Pulsatile vs continuous: the shape of the signal
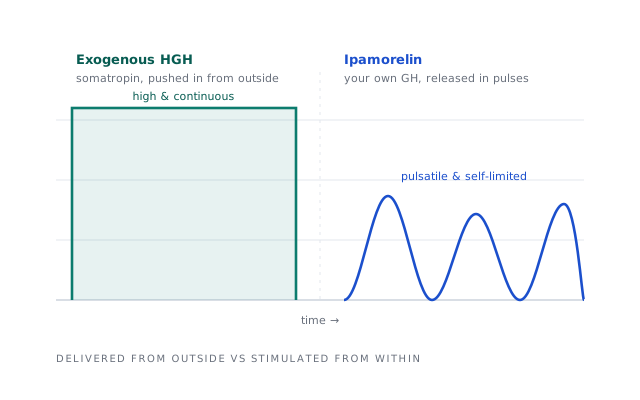
Healthy growth-hormone release is not a steady drip; it comes in bursts, mostly overnight, with low troughs in between. Ipamorelin works with that rhythm — it elicits a pulse that rises and then subsides, leaving the between-pulse lulls the body uses to stay sensitive. HGH injected for non-medical use does the opposite: it holds the hormone elevated and continuous, often at supraphysiologic levels that erase the natural troughs. The contrast isn’t cosmetic. A continuous, feedback-free flood is the setting in which the classic harms of growth-hormone excess appear, while a self-limited pulse is far less likely to push the system into that territory.
Magnitude: HGH is in a different weight class
It would be misleading to frame ipamorelin as “HGH lite.” Injecting the hormone directly delivers a far larger and more reliable rise in growth hormone and IGF-1 than coaxing a pulse out of the pituitary ever could — the secretagogue is capped by how much your own gland is willing and able to release, and by the feedback that shuts the pulse down. The evidence base matches that gap: HGH’s effects (and limits) have been characterized in controlled human studies. A systematic review of 27 randomized study samples in young, fit adults (303 given GH) found lean body mass rose 2.1 kg (95% CI 1.3 to 2.9 kg), but strength and exercise capacity did not seem to improve, and edema and fatigue were more common.[3] Ipamorelin’s human therapeutic record is thin by comparison. Its headline data is animal pharmacology showing it is the first selective secretagogue: in pigs it raised GH without the ACTH and cortisol rise seen with older GHRPs.[2] Its only randomized trial in patients, a week of IV dosing after bowel surgery (n = 114), found no significant benefit over placebo (median time to a tolerated meal 25.3 vs 32.6 hours, p = 0.15).[6] Different strength, and a very different depth of evidence.
Swipe to see all columns
| Attribute | HGH (somatropin) | Ipamorelin |
|---|---|---|
| What it is | Recombinant human growth hormone — the hormone itself | A peptide secretagogue that triggers your own GH release |
| Source of the GH | Exogenous — injected from outside | Endogenous — released by your own pituitary |
| Signal shape | Continuous, often supraphysiologic when misused | Pulsatile and self-limited; feedback stays intact |
| Relative potency | Far stronger and more reliable | Milder; capped by your own gland and feedback |
| Approval status | FDA-approved for specific GH deficiencies only | No approved therapeutic use |
| Anti-doping status | Banned by WADA; common abuse target | Banned by WADA as a GH secretagogue |
| Documented harms | Edema, carpal tunnel, insulin resistance, acromegalic change; rare fatal overdose | Smaller; long-term safety largely untested |
Risk profile follows the model
The harms of HGH are not theoretical — they are the well-documented consequences of holding growth hormone high. Excess somatropin causes fluid retention and edema, carpal tunnel syndrome, joint pain, insulin resistance and impaired glucose tolerance, and, over time, the coarsened, acromegalic features of true growth-hormone excess. A systematic review of randomized trials covering 220 healthy older adults on GH found them significantly more likely to get soft-tissue edema, joint pain, carpal tunnel syndrome and breast enlargement, and somewhat more likely to develop diabetes or impaired fasting glucose. The body-composition payoff was small: 2.1 kg of lean mass gained and 2.1 kg of fat lost, with body weight unchanged, and the authors concluded GH cannot be recommended as an anti-aging therapy.[4] At the extreme, injected HGH can kill: there is a published case of fatal overdose from growth-hormone injection.[5] That is the cost of bypassing the body’s controls.
Ipamorelin’s risk picture is smaller and gentler — because the pulse is self-limited, it is far less likely to drive the chronic, supraphysiologic state behind those harms, and in animal studies its selectivity left ACTH and cortisol alone.[2] But “gentler” is not “proven safe.” The honest caveat is that ipamorelin has no long-term controlled human safety data, and it still nudges the same GH/IGF-1 axis whose chronic elevation carries the long-standing theoretical concerns about tissue growth. The FDA also notes a published report of serious adverse events, including death, when ipamorelin was given intravenously for gut motility.[7] Lower risk, yes; established safety, no.
Legality and anti-doping: both are off-limits in sport
HGH is a prescription drug. Outside a documented medical indication, possessing or distributing it for performance or anti-aging use is illegal in many jurisdictions, and it is one of the most familiar targets of athletic doping programs. Ipamorelin is not a sanctioned alternative escape hatch: as a growth-hormone secretagogue it sits on the same prohibited list.[8] Nor can a regular pharmacy compound it: on the FDA’s list as updated in April 2026, ipamorelin for 503A pharmacies is “nominated but withdrawn” (not on the bulks list), and it stays in Category 2 for 503B outsourcing facilities.[7] So the “which is allowed” question has a flat answer for competitive athletes — neither. The only legitimate growth-hormone therapy is prescribed somatropin for a diagnosed deficiency, under medical supervision.[1]
Which fits which goal — an honest verdict
If there is a genuine, diagnosed growth-hormone deficiency, the answer isn’t a peptide at all — it’s prescribed HGH, the approved treatment, managed by a clinician.[1] If the interest is the gentler, “work-with-my-own-rhythm” secretagogue approach, ipamorelin is the milder, pulsatile, feedback-preserving option — usually paired with a GHRH analog like CJC-1295 rather than used alone, and always with the understanding that its strength and its safety record are both far smaller than HGH’s. We cover that pairing in the ipamorelin & CJC-1295 evidence review, and how ipamorelin compares to the GHRH-analog peptides in ipamorelin vs sermorelin. What no goal changes is the ceiling: in healthy adults, neither HGH nor ipamorelin has been shown to reverse aging, and the GH/IGF-1 bump each produces is a biomarker, not a proven outcome.[4]
The honest bottom line
HGH and ipamorelin are not two doses of the same thing — they are the hormone versus a request for the hormone. HGH is the real, far more potent, far better-studied molecule, injected from outside, approved only for specific deficiencies, and carrying documented harms when pushed supraphysiologic. Ipamorelin is a milder secretagogue that stimulates your own pulsatile release, preserves feedback, and has a smaller but largely untested risk profile and no approved use. Ipamorelin is not an HGH equivalent, and neither is a proven anti-aging tool. To sit the wider peptide field side by side on evidence grade, use our peptide evidence matrix.